
Report hypotension, tachycardia, and signs of hypovolemic shock from excessive fluid loss immediately.
Before you read
Test yourself first: 3 questions
Question 1 of 3
A client with diabetes insipidus is at greatest risk for:
Answer: B. Diabetes insipidus causes massive output of dilute urine → dehydration, hypernatremia, and hypovolemia. Monitor I&O, daily weight, and replace fluids; desmopressin may be given.
Question 2 of 3
A client develops diabetes insipidus after neurosurgery. Which finding does the nurse expect?
Answer: A. Diabetes insipidus results from a deficiency of (or resistance to) ADH, causing the kidneys to excrete large volumes of dilute urine. Expected findings include polyuria with very low urine specific gravity, excessive thirst, hypernatremia, and risk of dehydration.
Question 3 of 3
A nurse is reviewing diagnostic criteria for diabetes mellitus. Which fasting plasma glucose value is diagnostic of diabetes?
Answer: B. A fasting plasma glucose of 126 mg/dL or higher (on more than one occasion or with confirmation) meets the diagnostic criterion for diabetes. A fasting value of 100 to 125 mg/dL indicates prediabetes (impaired fasting glucose), and values below 100 mg/dL are normal. An A1c of 6.5% or higher is also diagnostic.
Keep the streak going with more questions like these, each with a full rationale.
What is diabetes insipidus?
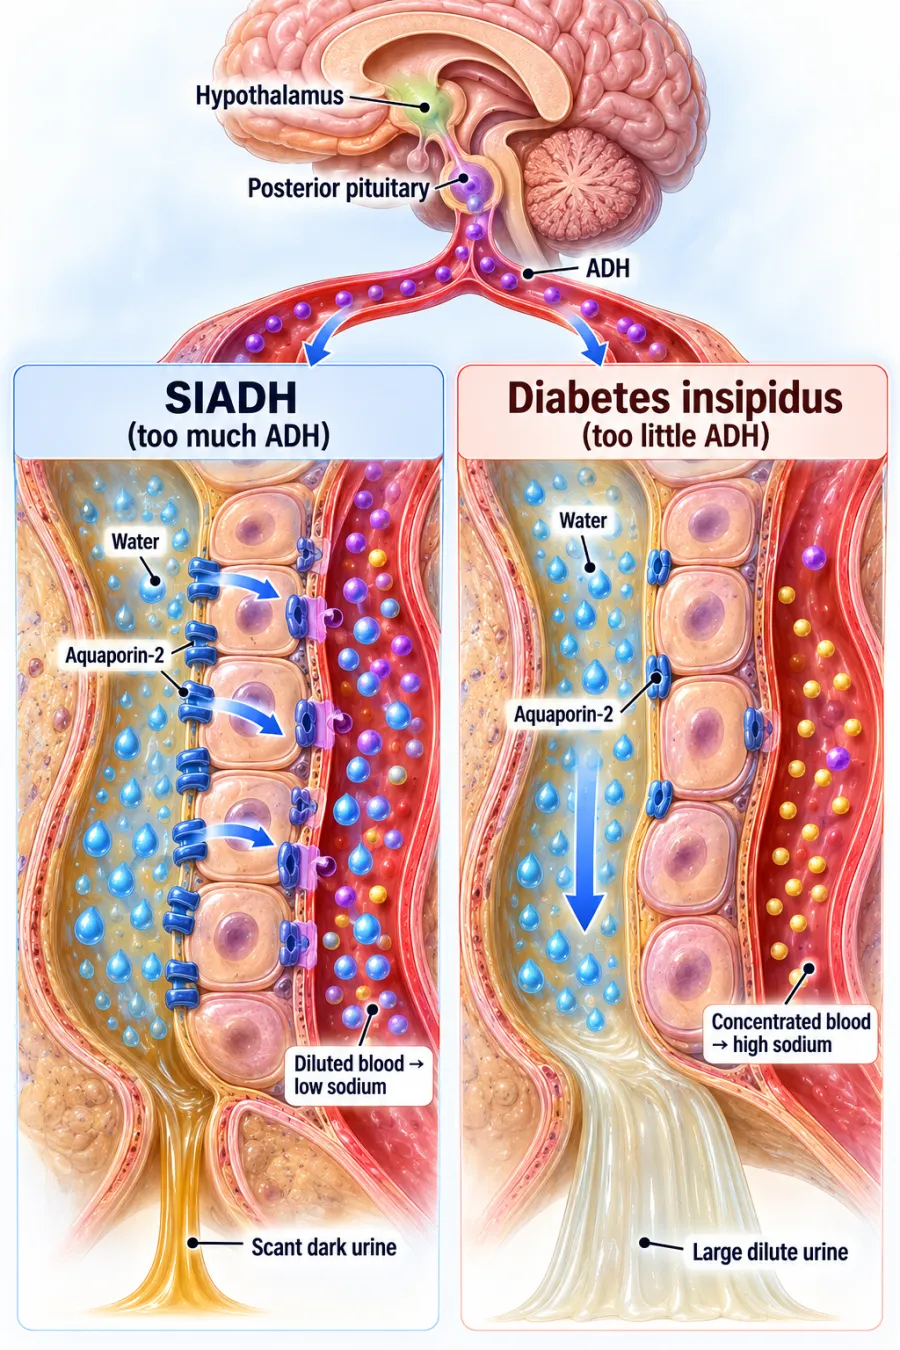
Causes include head trauma, brain/pituitary surgery, tumors (central DI), or kidney resistance to ADH (nephrogenic DI). Despite the name, it is unrelated to blood sugar. Memory aid: DI = 'Dry Inside' (too much water lost); it is the mirror image of SIADH.
Diabetes Insipidus illustrated
Key points to remember
- Hallmark findings are massive output of dilute urine (polyuria, often 4-20 L/day) and intense thirst (polydipsia).
- Urine is very dilute with low specific gravity, while serum is concentrated with hypernatremia.
- Excessive water loss causes dehydration, hypotension, tachycardia, and weight loss.
- Serum osmolality is high while urine osmolality is inappropriately low.
- If thirst is impaired or fluids are inaccessible, severe dehydration and hypovolemic shock can develop rapidly.
Signs & symptoms
- Polyuria 4-20 L/day, dilute urine
- Polydipsia, dehydration, ↑ Na
- Low specific gravity <1.005
Nursing priorities
- Replace fluids to match output and monitor strict intake/output, daily weights, and urine specific gravity.
- Administer desmopressin (DDAVP) for central DI as ordered and monitor for response and for water intoxication.
- Monitor serum sodium, neurologic status, and signs of dehydration and hypovolemia closely.
- Encourage fluid intake and keep water readily available to alert patients.
- Monitor for hypovolemic shock and maintain IV access for fluid replacement.
Labs & values
Patient teaching
- Take desmopressin exactly as prescribed and report excessive thirst, headache, or weight changes.
- Carry water at all times and respond promptly to thirst to prevent dehydration.
- Wear medical alert identification and weigh yourself daily, reporting rapid changes.
Red flags: report now
- Report hypotension, tachycardia, and signs of hypovolemic shock from excessive fluid loss immediately.
- Report urine output greater than 200 mL/hr for several hours or persistently very dilute urine.
- Watch for desmopressin overcorrection causing water retention and hyponatremia.
References
Clinical references for this topic

